

Lab Team
Available as a licensed medicine and available as a research compound are separate questions with opposite answers. Conflating them causes most of the confusion.
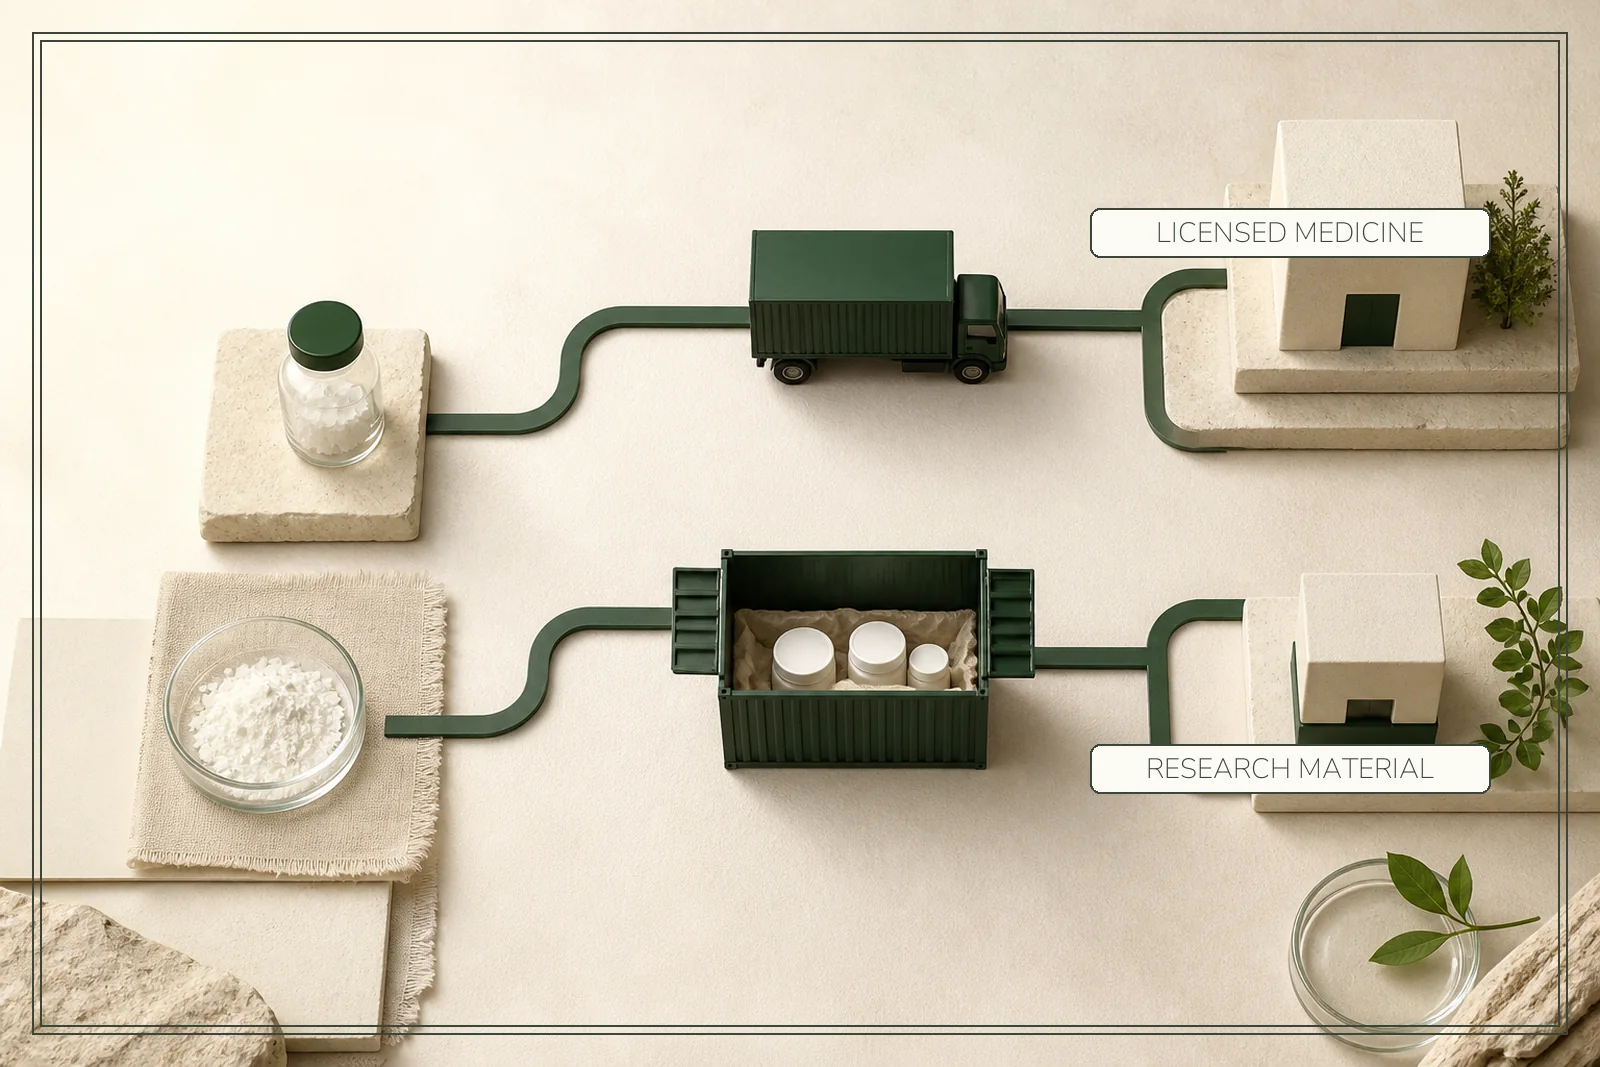
Almost all confusion about retatrutide availability comes from the word carrying two meanings at once. Available as a licensed medicine and available as a research compound are separate questions with different answers, different supply chains and different legal footings. Answer them separately and the picture becomes straightforward. Answer them together and it becomes contradictory.

Is retatrutide available as a licensed medicine?
No, nowhere, and not soon.
No medicines regulator in Britain, Europe or the United States has authorised retatrutide for sale. Its phase 3 clinical programme is ongoing, and that work must complete and be assessed before any regulator can consider authorising it. No pharmacy in any of those territories can dispense it, and no prescriber can issue it as an approved product.
The sequence is fixed and slow by design. Phase 3 completion, data submission, regulatory assessment, and only then a marketing authorisation with an approved indication and a brand name. Each stage takes substantial time, and none of it can be skipped.
It is worth knowing what that answer rules out, because the question is often really about something else. There is no early-access route to a compound at this stage that operates like a shortened version of the normal one. Programmes that supply unauthorised compounds to individuals exist, but they are narrow, clinician-initiated and tied to specific circumstances rather than open to anyone who has read about a trial. For practical purposes, the licensed route to retatrutide does not currently exist in any form.

Is retatrutide available as a research compound?
Yes, and this is a genuinely different supply route rather than a workaround of the first one.
Research chemical supply exists to serve laboratory work, and it operates under a different legal basis from medicinal supply. Material is sold for research use only, is not authorised for human use, and carries no medicinal claims. That distinction is not a formality or a disclaimer bolted onto a consumer product, and what the research-use-only designation covers legally is worth reading in full. It defines what the material is and what may lawfully be said about it.
In practical terms the route is short, which is both its convenience and its weakness. Material is bought directly from a supplier, with no prescriber, no pharmacy and no intermediary of any kind between the seller and the buyer. Every party that a medicinal supply chain inserts specifically to catch problems is simply absent, and what remains is a transaction between two people, one of whom knows what is in the vial.
The practical consequence is the one covered elsewhere on this site: in the absence of regulatory batch release, verification falls entirely to the supplier's own documentation. No regulator stands between the vial and the buyer.

Why does conflating the two cause so much worry?
Because it produces a frightening conclusion from a false premise.
The reasoning usually runs: this is not approved anywhere, therefore anything I can find must be counterfeit. The first half is true. The second does not follow. Research chemical supply is a real and long-standing category, and material sold within it can be exactly what it claims to be, provided the supplier documents it.
The correct inference from the absence of authorisation is not that all available material is fake. It is that no regulator has verified it, which shifts the entire burden of proof onto documentation you can inspect yourself. That is a meaningfully different conclusion, and a more useful one.
The mirror-image error is just as common and rather more consequential. Having discovered that a legitimate research market exists, some readers conclude that the market's existence implies some form of official tolerance for what they intend to do with the material. It does not. The research category is defined by the purpose the material is supplied for, and it says nothing about any other purpose. Both errors come from the same conflation running in opposite directions, which is why separating the two meanings of "available" resolves both at once.
What happens to availability when phase 3 reports?
Nobody knows, and any source giving you a date is quoting an estimate rather than reading a schedule.
Three outcomes are possible and they are not equally discussed. The programme reports and a regulator authorises, at which point a licensed product exists with a brand name and a prescription route. The programme reports and authorisation is refused, delayed, or granted for a narrower indication than expected. Or the programme is discontinued. Compounds fail at phase 3 with some regularity, and an ongoing programme is a statement that the question is being asked, not that the answer will be favourable.
The dates that circulate are usually derived from trial registry completion estimates, and those estimates move. Registry completion is also not the same event as authorisation — submission and assessment follow it, and both take time that is not fixed in advance. Planning around a specific arrival date means planning around a figure that was never a commitment.
For research supply specifically, an authorisation would not abolish the research market; reference compounds remain research reagents regardless of what else exists. What it would plausibly change is the surrounding environment, since regulatory attention to medicinal claims tends to sharpen once there is an authorised product for such claims to undercut. That is a general pattern rather than a forecast about this compound.

What does availability not tell you?
Anything about the quality of a specific vial.
Availability is a statement about a market. It establishes that material can be obtained, and nothing whatsoever about whether any particular unit is pure, correctly identified, or intact on arrival. Those are properties of a lot, evidenced by documentation, and they vary enormously between suppliers within the same market.
Treating availability as reassurance is the error that follows from resolving the first confusion. Having established that legitimate supply exists, it is tempting to conclude that any supply is legitimate. It is not.
Nor does documentation settle it absolutely. Paperwork can be fabricated, and a certificate does not prove itself. What documentation creates is a published standard the supplier has paid to meet and can be measured against, which shifts the odds substantially without ever reaching certainty. We would rather say that than imply a guarantee no supplier in this market can honestly offer.

What does "in stock" mean for a research supplier?
That a lot exists and has not sold out. The phrase is a statement about inventory, and it carries no information at all about quality.
Research peptides are manufactured in discrete lots rather than produced continuously. A supplier commissions or buys a batch, holds it, sells through it, and then obtains another. So the phrase describes a particular batch sitting on a particular shelf, and when that batch runs out the replacement is a different manufacturing event with its own analysis and its own lot-to-lot variation.
That has a consequence most listings never surface. When the lot changes, the documentation should change with it. A product page displaying the same certificate month after month across several restocks is displaying a document that has stopped describing what ships — and because certificates rarely carry a prominent date, nothing about the page announces that it has gone stale.
It also makes permanent availability worth a second look rather than treating it as convenience. Continuous stock at a fixed price, with no visible turnover of lot numbers, points to one of two things: an unusually large single batch, or a supplier not tracking lot identity closely enough for it to show. Neither is proof of a problem. Both are worth one question, and it is a short one — which lot is shipping now, and is the published certificate that lot's?

What availability looks like when documented properly
If the burden of proof sits with the supplier, the only useful response is to publish the proof.
We supply retatrutide with per-lot certificates of analysis whose lot numbers match the vial, HPLC chromatograms rather than summary percentages, mass-spectrometry identity confirmation, and stated cold-chain shipping conditions. You can see what we currently hold on the retatrutide 20mg listing, with the current lot documentation linked from it.
The word "current" is doing deliberate work in that sentence. The certificate shown is the one for the lot presently shipping, and it is replaced when the lot is, which is the whole point of the question this article ended on. If you order and the document you received does not match the vial in front of you, that is a defect we would want raised with us directly, and it is a fair test of whether any supplier's documentation is a working practice or a page decoration. The supplier checklist sets out what to demand from anyone, ourselves included. Supplied for laboratory research use only.
For research use only — not for human consumption. Nothing here is medical advice.


